
Written by: Jorie Larsen Schroeder
Reviewed by: Nina Kalus, PsyD, and Yalda Safai, MD, MPH
Transcranial magnetic stimulation (TMS) and electroconvulsive therapy (ECT) are both considered effective, FDA-cleared neuromodulation therapies used to treat mental health conditions.
TMS is noninvasive and doesn’t require anesthesia; ECT involves controlled electrical stimulation that induces a seizure under general anesthesia.
ECT can give patients results quicker, so clinicians favor it for urgent or psychotic cases, while TMS is better suited for patients who aren’t in crisis.
TMS side effects are mild and can include scalp discomfort and headache; ECT can cause confusion, drowsiness, and short-term memory loss.
Transcranial magnetic stimulation (TMS) and electroconvulsive therapy (ECT) are both effective neuromodulation therapies used to treat a variety of mental health conditions. But when weighing ECT vs. TMS for depression, which is best to recommend to your patient, and when?
This article compares transcranial magnetic stimulation vs. ECT at the provider level. This side-by-side breakdown covers staffing, cost, side effects, efficacy, and more.
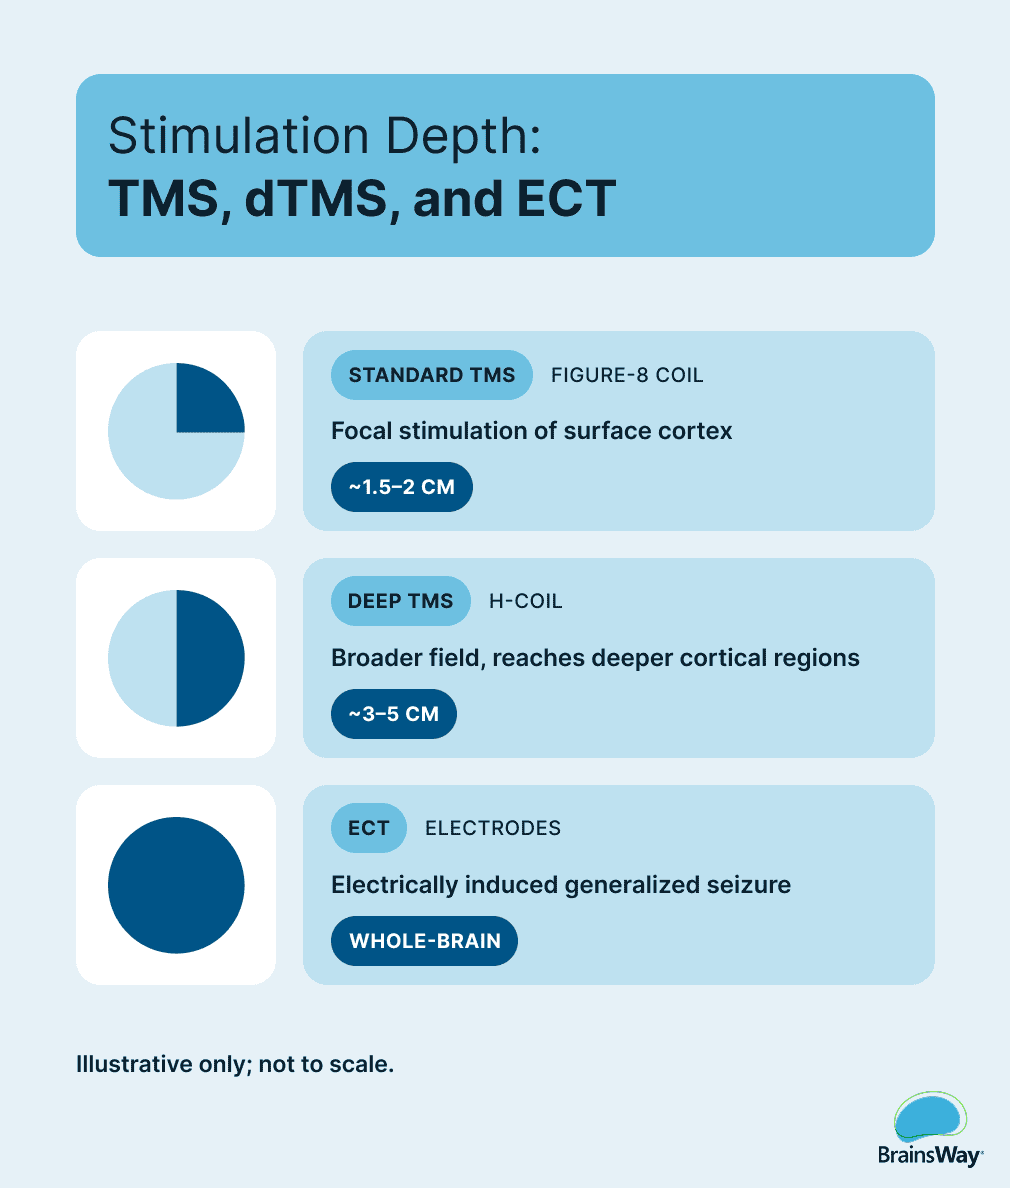
During standard (aka first-generation) TMS, a provider places an electromagnetic coil against the scalp. This sends brief pulses of magnetic energy through the skull to induce an electric current in the brain tissue.
Deep TMS follows the same mechanism of action; patients wear a BrainsWay-patented H-coil helmet. The main difference is that deep TMS penetrates deeper, up to 5 centimeters, into targeted brain tissue. When treating major depressive disorder, the coils are placed above the dorsolateral prefrontal cortex — that’s the region of the brain associated with mood regulation.
ECT uses controlled electrical currents to trigger a monitored seizure (lasting from 30 to 90 seconds, while the patient is under general anesthesia. The goal is to create therapeutic changes in the brain’s neurotransmitter systems and ultimately improve psychiatric symptoms.
TMS therapy is FDA-cleared to treat:
ECT is FDA-cleared to treat:
| ECT | Standard TMS | Deep TMS | |
|---|---|---|---|
| Mechanism | Uses electrical currents to induce a controlled seizure to affect the brain’s neurotransmitters. | Electromagnetic coil placed against the scalp induces magnetic energy that passes through the skull and induces an electric current in the underlying brain tissue. | Same as standard TMS, but the magnetic energy pulses are broader and deeper; they pass deeper into the brain’s structures, up to 5 cm. |
| Anesthesia required? | Yes | No | No |
| Facility/licensure level | Performed in a hospital or surgical center. | Typically performed in an outpatient clinic. | Typically performed in an outpatient clinic. |
| Staffing required | Psychiatrist, anesthesia provider, treatment and recovery nurses. | Prescribing physician and trained TMS technician. | Prescribing physician and trained TMS technician. |
| Session length | 5–10 minutes (plus 30–60 minutes of recovery). | 19–37-minute session. | 20-minute session. |
| Course length/total sessions | 2–3 treatments per week over several weeks. | 3–6 days per week, over a period of six to eight weeks. | 5 days per week, over a period of four to six weeks. |
| Response and remission rates | 66% response rate; 16.4% remission rate* | 58–83% response rate; 28–63% remission rate** | 38% response rate; 32% remission rate*** |
| FDA-cleared indications | Severe major depressive episodes associated with major depressive disorder (MDD) and bipolar disorder; catatonia. | Major depressive disorder; MDD with anxiety symptoms, commonly referred to as anxious depression; obsessive-compulsive disorder; migraines with aura; smoking cessation. | Major depressive disorder; MDD with anxiety symptoms, commonly referred to as anxious depression; obsessive-compulsive disorder; smoking cessation. |
| Side effects | Confusion, short-term memory loss, headache, nausea, drowsiness. | Mild scalp discomfort and headache. | Mild scalp discomfort and headache. |
*according to a 2023 study of 38 patients with major depressive disorder
**according to a 2020 study of 5,010 adults with major depressive disorder
***according to a 2015 study of 200 patients with major depressive disorder
Deep TMS is highly effective in treating major depressive disorder. In one 2015 study published in World Psychiatry, 38% of the patients receiving deep TMS responded to treatment, with 32.6% achieving remission. Deep TMS is also effective in treating OCD. In a 2019 study published in the American Journal of Psychiatry, 38% of participants showed significant clinical improvement of OCD symptoms over a six-week course.
For patients undergoing TMS treatment, symptom improvement is often gradual and cumulative. Some patients notice relief as early as two weeks in, while others find their symptoms improving toward the end of the treatment course.
ECT is known for its rapid symptom improvement; patients often respond within the first two weeks of treatment. It’s also highly effective: In a 2023 study published in BJPsych Open, 66% of the 1,100 patients with treatment-resistant depression responded to ECT.
When comparing ECT vs. TMS treatment, it’s not necessarily that one is superior to the other.
“It’s more about what is going to be a better fit for the patient in front of me,” explains Vinay Saranga, MD, psychiatrist at the North Carolina Institute of Advanced NeuroHealth. “If the patient is extremely depressed, suicidal, psychotic, and it’s a race against the clock, we’re probably going to favor ECT because it works fast and provides a powerful response. On the other hand, if the patient is depressed but not in an actual crisis, TMS would probably be more favorable.”
TMS side effects are generally mild, and most people report no significant side effects. About half of patients report a mild headache that gradually fades over the course of treatment. Some report mild scalp discomfort or facial twitches. Because TMS is noninvasive, patients can drive themselves to and from appointments and resume normal activities right after treatment.
“TMS is a much simpler process [than] ECT,” explains Dr. Saranga. “ECT is often done in a hospital setting under anesthesia,” he says, “which creates more risks. TMS, on the other hand, is done in the office, while the patient is awake, and has very few side effects..”
Because ECT requires general anesthesia and induces a seizure, its side effects can be more significant. Common ones include confusion, nausea, and drowsiness, as well as short-term memory loss and headache. Confusion usually resolves within 30 minutes of the procedure, whereas memory loss can take a bit longer to resolve. Permanent memory loss is rare.
ECT patients face a longer recovery than TMS patients and need someone to drive them home after each session.
For providers, ECT’s risk profile means a lengthier informed consent process and pre-treatment medical evaluation, while TMS screening is usually quicker and centers on a contraindication checklist.
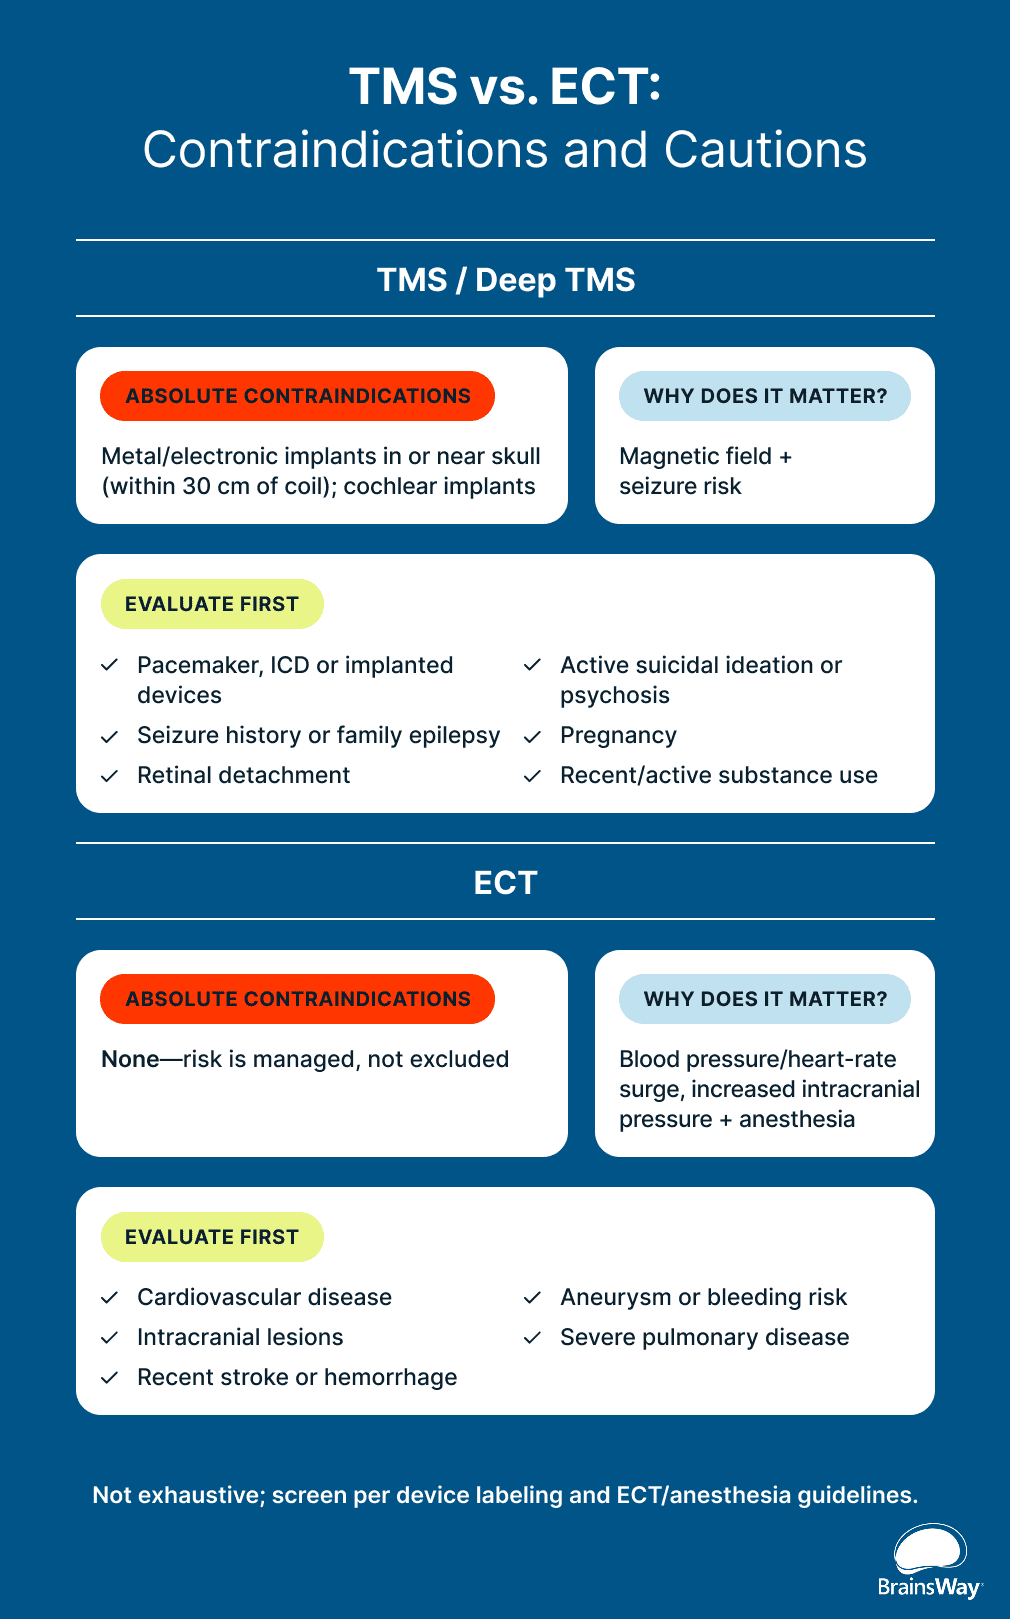
Absolute contraindications for TMS include:
Patients with the following conditions require further evaluation before starting TMS treatment:
There are no absolute contraindications for ECT. However, its side effects can make treatment riskier for certain individuals.
Conditions that require further evaluation before starting ECT include:
TMS is performed on an outpatient basis within a clinic. The trained practitioner runs a motor threshold test to determine the minimum amount of energy required to make the patient’s finger twitch, which sets the appropriate stimulation parameters.
Then, the patient sits awake and alert in a comfortable chair for the duration of the session, which varies in length depending on which TMS protocol the patient receives. A deep TMS session typically lasts 20 minutes, and treatment is five days a week, for about four to six weeks. Because it’s noninvasive, the patient can drive themselves to and from appointments.
ECT, by contrast, usually takes place in a hospital or surgical center. The patient typically fasts before the procedure, and then receives an IV, muscle relaxants, and general anesthesia. Then, the physician places electrodes on the scalp and administers brief electrical stimulation to the brain to induce a controlled seizure.
As mentioned above, recovery from ECT takes longer than with TMS, because the patient must wake up from general anesthesia under supervision and be monitored afterward. Patients are not allowed to drive themselves home from the appointment. A typical ECT course is two to three treatments per week over several weeks.
The main capital investment for TMS is the upfront cost of the machine. A BrainsWay Deep TMS device can range from $100,000–$150,000, depending on the coil/system category, cooling method, features, and business model (outright purchase, leasing, pay-per-use, etc.). A standard TMS machine tends to cost less than a deep TMS machine.
An ECT device often costs less than a TMS machine, but the real expense comes from everything around it: anesthesia equipment, monitoring devices, emergency cart, and recovery area, for example.
With TMS, a physician prescribes and oversees treatment, while trained technicians deliver the daily sessions in an outpatient office.
“Practices need to consider who will be managing the TMS service line and educating staff about TMS. If a practice doesn’t have someone in-house who can truly own TMS training, they can always outsource,” advises Ben Spielberg, MS, PhD candidate, and founder and CEO at Solstice Training Institute.
With ECT, the procedure is typically performed in a hospital or surgical center. Staffing includes a psychiatrist to determine dosing and administer the treatment, an anesthesiologist to provide general anesthesia, and treatment and recovery nurses.
Multi-location medical groups often centralize ECT treatment at one hospital-affiliated hub, because of anesthesia and facility requirements.These groups tend to offer TMS more widely because the device fits easily in a standard doctor’s office.
For smaller practices, TMS is the more realistic fit, and physicians should refer patients to a hospital for ECT.
For many psychiatrists, ECT is the first recommendation for severe or acute depression. TMS, on the other hand, best suits patients with treatment-resistant depression who don’t want to disrupt their lives with anesthesia several times per week.
“When someone is in immediate danger, stabilizing them becomes the top priority,” says Dr. Saranga. “Once they’re safe and showing improvement, then we can think about longer-term treatment and maintenance.”
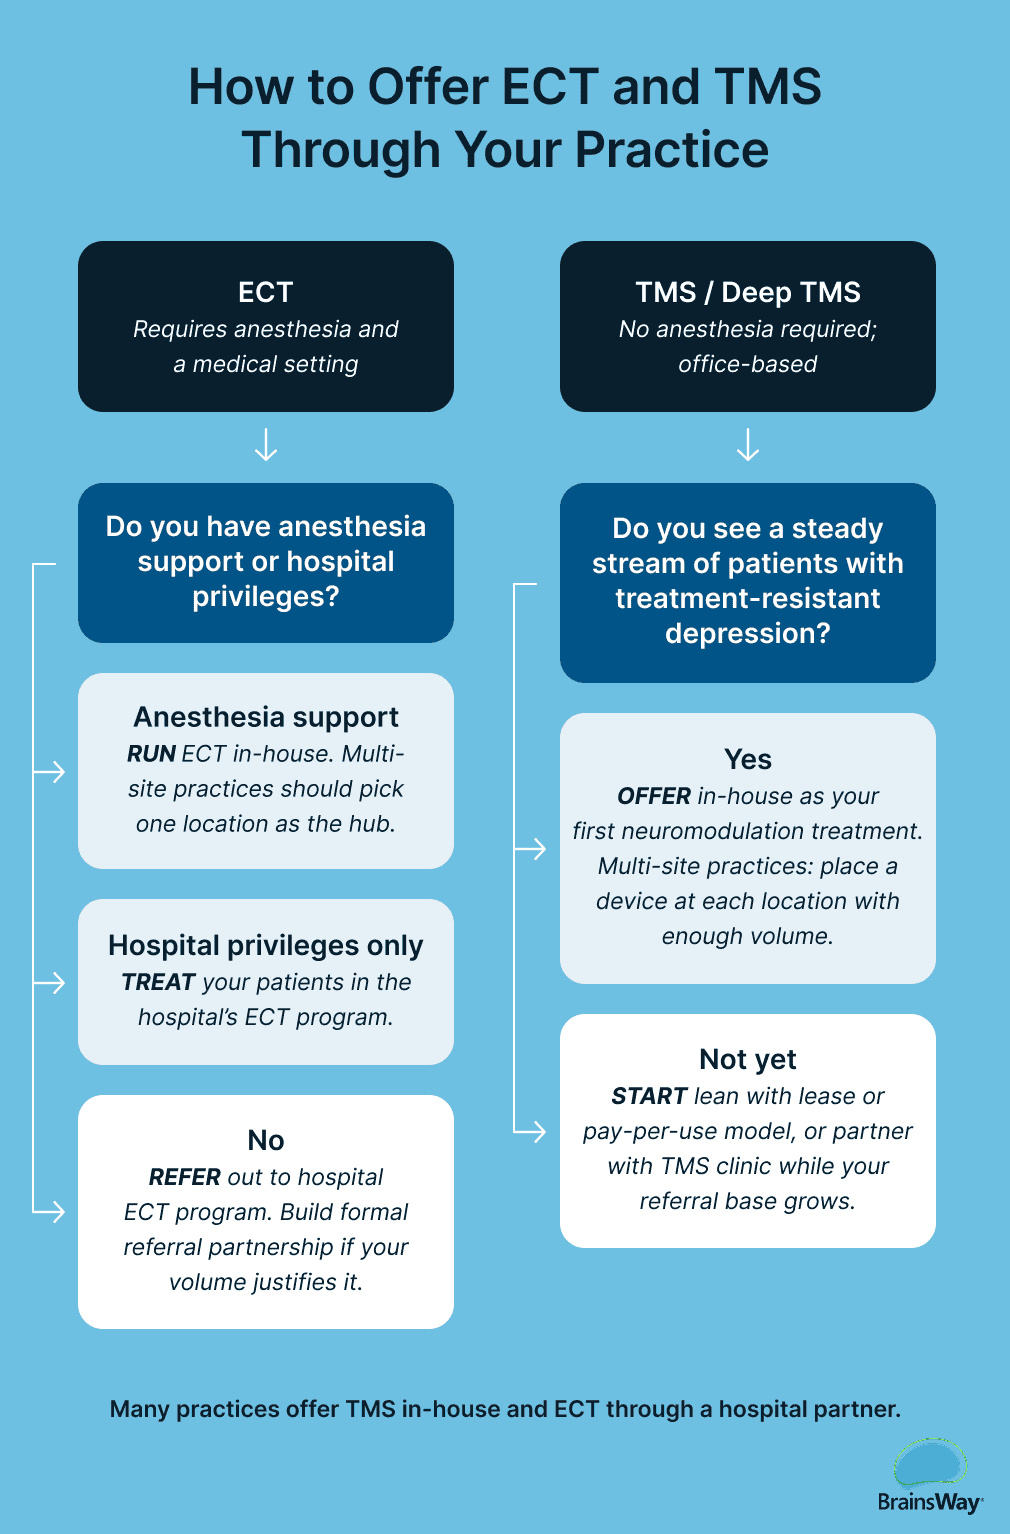
Both ECT and TMS are highly effective at helping to relieve symptoms associated with major depressive disorder and other mental health conditions. Each patient’s history, tolerance for side effects, and lifestyle ultimately affect which treatment is the right next step. Your medical group’s size, location, and staffing will help determine which treatment makes the most sense to offer in-house.
TMS is not as well-known as some depression treatments — but that’s changing, as are some of the general misconceptions patients have regarding brain stimulation therapy. As the science behind TMS continues to show strong benefits, more psychiatrists refer their patients to TMS clinics or purchase a TMS device for their own practice.
ECT carries an outdated stigma as “the last resort” for treatment-resistant depression, but that isn’t accurate. ECT is particularly effective in treating patients experiencing severe major depressive episodes associated with major depressive disorder and bipolar disorder.
ECT is often the first-line treatment for more urgent psychiatric cases, because results can appear within the first two weeks of treatment. “When someone comes to me and they are in such bad shape, they’re suicidal or experiencing psychosis and need immediate intervention, ECT wouldn’t be so far down on the list,” adds Dr. Saranga.
Both TMS and ECT effectively treat major depressive disorder, among other mental health conditions. TMS uses magnetic pulses while the patient is awake and alert, with no anesthesia and only mild side effects. ECT uses electrical stimulation to induce a controlled seizure under general anesthesia, with side effects that can include drowsiness, confusion, and short-term memory loss.
Absolute contraindications that disqualify a patient for TMS include metal or electronic implants in the skull and cochlear implants.




